Mental Health and Stigma
MODULE 2
1. Introduction to Stigma
1.1 Defining Stigma
Stigma concerning mental health can be difficult to define. Watch this TedTalk to gain an introduction to what stigma is, and how we can reduce the stigma surrounding mental illness.
Stigma in the Context of Mental Health
Stigma is one of the major barriers to accessing mental health treatment. It can impede social interaction, lower quality of life, interfere with social roles, and prevent timely access to treatment (Centre for Addictions and Mental Health, n.d.). This creates a cycle of disadvantage. Recently, anti-stigma efforts have increased in many countries, including many taking place in Canada.
1.2. Types of Stigma
There are many different types of stigma including public, or social, structural, and self-stigma. Some also consider there to be a fourth type: stigma-by-association. Click through the grid below to learn the basic definitions of each.

Public Stigma
The typical definition of stigma which highlights the views of the public towards mental health issues or a specific condition.
click to flip
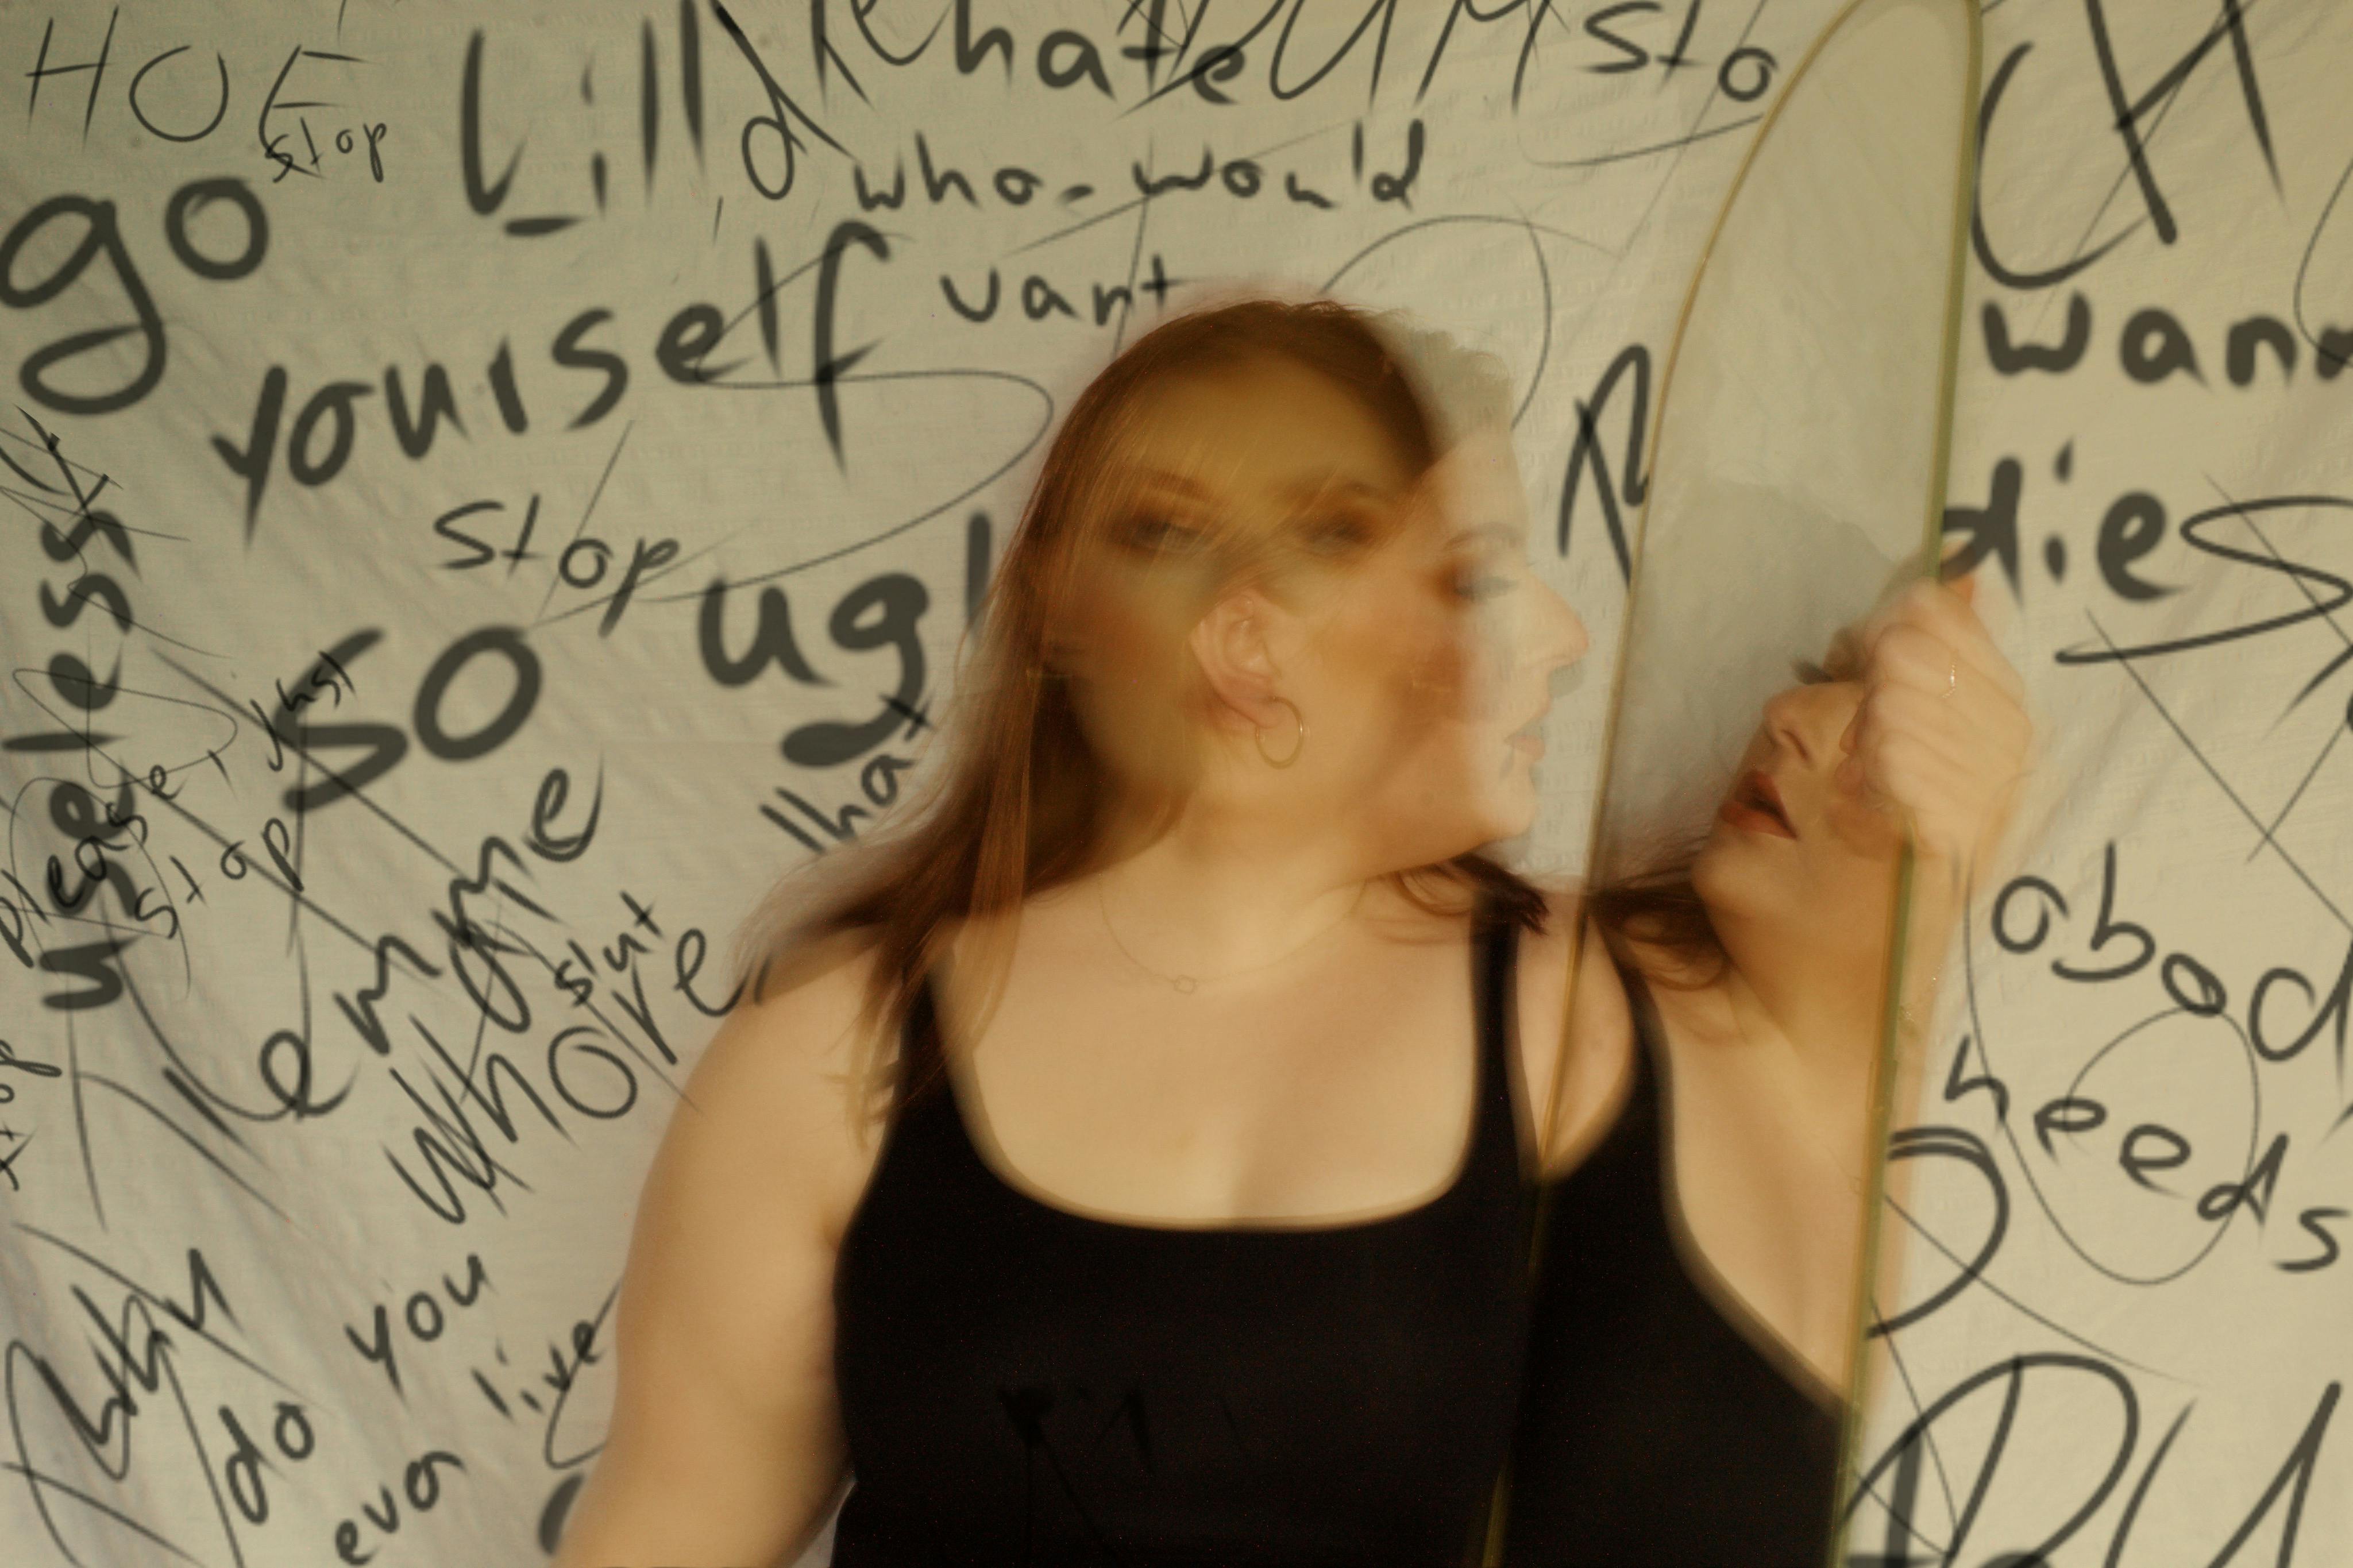
Self-Stigma
Occurs when an individual internalizes the negative stereotypes associated with their illness.
click to flip

Structural Stigma
In the context of mental illness, structural stigma refers to the rules, policies, and practices of social institutions that arbitrarily restrict the rights of, and opportunities for, people with mental illnesses.
click to flip

Stigma-by-Association
Involves stigma towards an individual based on their associations with stigmatized persons (i.e., someone experiencing a mental illness).
click to flip
1.2.1 Public Stigma
Public stigma is what most people think of when they say “stigma”. Public stigma highlights the views of the public towards mental illness or a specific condition.
- Includes public stereotypes and prejudicial attitudes toward people with mental illness
- Stems from a history of considering those suffering from mental illness to be “mad and to”taint” the family, since it was considered hereditary
This type of stigma can pose serious, negative implications to individuals struggling with their mental health. For example, a public stigma surrounding mental illness is that people with mental illness are dangerous, incompetent, unstable and may even be the one to blame for their disorder. Though this seems like just an idea, these public stereotypes can have serious consequences on the lives of people living with mental illnesses, and are the basis for many discriminatory practices.
As a result of these stereotypes, discrimination may take place in the form of employers refusing to hire individuals living with a mental illness, landlords refusing to rent to them, and even healthcare systems offering lower standards of care.
Examples of Public Stigma
Let’s check out some examples of public stigma experiences.

Stigma in Healthcare Settings
Mental healthcare providers are said to contribute largely to public stigma through their behaviours towards patients seeking help.
Individuals who seek services from mental health professionals often rate these providers as being among the most stigmatizing groups they encounter.
Among reports include being patronized, excluded from decisions on treatment, assumed to lack the capacity to be responsible for their lives, told their hope for recovery is limited, and told they will never work in regular careers, complete school, or even be a parent.

Stigma from Friends and Family
Friends and family are also reported sources of public stigma towards individuals living with mental illnesses.
Individuals with lived experience of mental illness report friends and family members views towards their loved one appeared to change upon the discovery of their mental illness. The majority of this change is often the result of social stigma. Friends and family may experience shame and/or fear that a scandal would occur if others find out that they are friends with/related to someone with a mental illness.
Typically, the more severe the illness, the stronger these feelings are. Additionally, feelings of embarrassment and shame are often accentuated in cases where the mental illness in question is addiction or substance use.
1.2.2 Self-Stigma
Self-stigma occurs when an individual internalizes the negative stereotypes associated with their mental illness. This means they begin to believe the negative social conceptions held by society surrounding their condition. Individuals experiencing a mental illness report experiencing stigma as even more limiting and devastating to their lives than their illness. The negative consequences of self-stigma are far reaching, including reductions in self-esteem and self-efficacy, leading to more negative thoughts and in some cases, even suicidal ideation.
Self-stigma occurs when an individual living with a mental illness has thoughts such as, “I am incompetent and incapable and it’s my fault I’m not getting better.”
Labeling Theory
Labeling theory is a perspective that goes hand-in-hand with self-stigma and has been proposed as an explanation for its occurrence. Labeling theory states that diagnosing an individual with mental illness places a label upon them and they feel they are associated with any societal implications of being mentally ill, such as being incapable or dangerous. Eventually, the feelings of bearing the burden of society’s negative stigma lead to an individual attempting different defensive behaviours to prevent society’s rejection and further judgement. These defensive behaviours may include hiding their treatment or withdrawing from it as well as disengaging in social interactions. These result in more unfortunate circumstances such as higher unemployment rates and reduced social relationships.
1.2.3 Structural Stigma
Structural stigma occurs in the context of mental health when laws, policies, and practices of institutions result in unfair treatment of those with mental illness. While it often occurs unknowingly (through implicit cognitive biases), it expresses the inequities embedded in the fabric of our social institutions, organizations, and our shared ways of thinking and acting. It is further manifested through cycles of blame, shame and mistrust for individuals who seek help for their mental illness or addiction.
Finding a way
This type of stigma is especially harmful to those with lived experience of mental illness. It can result in inequitable access (including housing, employment, etc.) and a lower quality of healthcare for these individuals, whether their concerns are related to physical health, mental health, and/or substance use.
1.3. Consequences of Stigma
Stigma can have consequences at both the individual and societal levels, including but not limited to: 1) barriers to treatment, 2) unemployment, and 3) intersectional consequences.
1.3.1 Barriers to Treatment
Despite recent advancements in reducing the stigma surrounding common mental health challenges like anxiety and depression, barriers to treatment remain. Below, we’ve organized these into barriers that individuals living with mental illness may face before, during, and after receiving a diagnosis and/or treatment.
TedTalk: Stop the Stigma
In this video, Heather Sarkis speaks about why it is important to openly talk about mental health and mental illness.
1.3.2 Unemployment
Most people with mental illnesses or mental health concerns are willing and able to work, but are often unable to due to factors outside their control.
In 2017, Statistics Canada found that of people surveyed with a mental health-related disability, less than half (46%) were employed. This demonstrates a significant unemployment rate for individuals living with a mental illness. Furthermore, more than half of the people surveyed who reported living with a mental illness believed they were disadvantaged in terms of employment due to the stigma surrounding their condition.
The stigma of mental illness causing unemployment results in detrimental consequences. Employment provides not only income and financial stability but also daily routine and structure, social interactions, a sense of achievement and purpose, and a sense of identity.

Social Stigma and Unemployment
Social stigma is an underestimated contributing factor to unemployment in people with mental illness or mental health issues: read this position paper published in BMC Psychology to learn more.
1.3.3 Intersectional Consequences
Issues related to stigmatization are multiplied for people who are additionally stigmatized for other reasons, including race, gender, sexuality, and more. For more information on mental health and the stigma surrounding marginalized groups, we recommend you check out our module on Mental Health and Intersectionality.
1.4 Section Summary
- Stigma is a major barrier to accessing mental health treatment for those who might be in need of it.
- Stigma can take many forms, including public stigma, self-stigma, structural stigma, and stigma-by-association.
- The consquences of stigma are far reaching, including stigma itself serving as a barrier to treatment / help-seeking, unemployment, as well as intersectional consequences for those who are additionally stignatied for other characteristics.
2. Anti-Stigma Interventions
2.1 Stigmatizing Language
Sometimes individuals unknowingly contribute to the stigmatization of mental illness in subtle ways. Such ways may include using derogatory terms and/or phrases in conversation. There are many stigmatizing phrases and terms used that are often used without the realization that they are contributing to the stigma around mental illness.
The language we use every day matters, and it is important to be sensitive to those living with mental illnesses. Common stigmatizing words or phrases to avoid include: “That made me wanna kill myself”, “I’m so bipolar”, or “My boss is really OCD.”
Many common phrases - like those depicted above - demean mental illnesses and contribute to the overall stigmatization of them in society. Though they are common phrases and may appear harmless on the surface, their common use increases both public stigma in society as well as the self-stigma a person living with a mental illness may internalize.
A person with lived experience of mental illness may hear comments like these and reflect more negatively on themselves, or choose not to reach out to their support network as a result of feeling that people view their illness as a joke. These seemingly harmless words can “downplay” serious illnesses, and are insensitive to those who live with mental illnesses day in and day out.
Combat Mental Health Stigma with Language Shifts
This resource from the Mental Health Commission of Canada discusses ways to reduce stigma in our conversations.
2.2 Mental Health Literacy
For any hope to eradicate mental health stigma, steps must be taken to address stigma on several levels. This includes addressing it at the level of specific individuals, their social interactions with others, and on the large-scale level of society. One way to do this is by improving mental health literacy.

What is Mental Health Literacy?
Overall, the development of mental health literacy (MHL) came from health literacy, which was informed by the universal and concrete observation that low functional literacy in regard to any form of health is associated with endless poor health outcomes. MHL was originally conceptualized as “knowledge and beliefs about mental disorders which aid their recognition, management, or prevention” (Kutcher et al., 2016). It was then refined to include knowledge that benefits the mental health of others and it became important to also focus on the health promotion aspect of MHL.
Over years of evolving and refining definitions, this eventually led to the most recent definition of MHL: “understanding how to obtain and maintain positive mental health; understanding mental disorders and their treatments; decreasing stigma related to mental disorders; and, enhancing help-seeking efficacy” (Kutcher et al., 2016).
Learn more about Mental Health Literacy
Visit mentalhealthliteracy.org to learn more and to access toolkits and resources related to mental health literacy.
Previous definition
"Knowledge and beliefs about mental disorders which aid their recognition, management, or prevention."
Updated definition
"Understanding how to obtain and maintain positive mental health, understanding mental disorders and their treatments, decreasing stigma related to mental disorders, and enhancing help-seeking efficacy."
Good mental health literacy in young people and their key helpers may lead to better outcomes for those with mental disorders, either by facilitating early help-seeking by young people themselves, or by helping adults to identify early signs of mental disorders and seek help on their behalf.


Mental Health Literacy and Stigma
Most research on the subject shows that mental health literacy does not directly combat stigma when you consider the stigma that exist due to existing prejudices and discrimination. Often, people ignore available information that contradicts their existing beliefs. Instead, mental health literacy aims at correcting misconceptions with factual information.
A primary way to intervene early by implementing MHL within schools. This can be done through a third-party organization, or through the school’s teaching staff after they have been educated on the content themselves. Many studies have shown a significant improvement in overall mental health knowledge and help-seeking behaviour.
MHL can also be implemented in other aspects of life, such as informational campaigns, in the workplace (such as within new employee training, company-funded MHL seminars, etc.), and at home. At home, parents should become well-versed with MHL in order to educate their children and have conversations within the home about mental health.
2.3 Mental Health Education
Educational approaches to ending stigma present facts about the condition with the aim to correct any misinformation or contradicting negative attitudes or beliefs. There are a mass number of stereotypes and misconceptions regarding mental illness/disorder and can vary in content and severity based on the specific type of mental illness/disorder.
Stereotypes
Stereotypes are incredibly harmful to both the person dealing with mental health issues as well as the people who are supporting them. Stereotypes often stem from misunderstanding and fear, but can generate a large number of issues for others (Oexle et al., 2018). Explore some examples of the negative impact of stereotypes below.

Not Seeking Help
Not seeking help due to fear of being judged, losing their job, or internal feelings of inadequacy/blame.
click to flip

Loss of Hope
Reduced hope of recovery or improvement and reduced likelihood of sticking with treatment, possibly due to stereotypes such as “people with mental illness will never fully get better” or “people with mental illness are to blame for their struggles”.
click to flip

Fear of Judgement
Difficulty in social situations or sharing comfortably about mental health problems due to fear of judgment, fear, or misunderstanding. 42% of Canadians were unsure whether they would socialize with a friend who has a mental illness (Mental Illness and Addiction, n.d.).
click to flip

Bullying
Increased bullying and/or physical harassment or violence from others due to stereotypes stemming from misunderstanding and fear.
click to flip
Debunking Stereotypes
Many stereotypes can be “debunked” (exposed and unlearned) through an educational approach. Using the information you have learned so far, try to debunk the following stereotypes.
TedTalk: Overcoming Mental Health Stereotypes Overcoming mental health stigma and stereotypes is difficult. The TedTalk below shares one woman’s story of doing just that.
2.4 Other Ways to Reduce Stigma
It is important to target the behavioural outcomes of the stigmatization process (discrimination and social inequity), which is consistent with rights-based or social justice models that emphasize social and economic equity for those with disabilities (such as equitable access to services, education, work etc.). For example, it is important to create alliances with researchers and program evaluators in order to critically evaluate anti-stigma activities and build better, evidence-based practices.
In this section, we will learn about 3 different types of interventions designed to reduce stigma: 1) awareness-raising, 2) contact-based, and 3) peer advocacy and services.

Awareness-Raising Interventions
This type of intervention is typically a multi-factored approach and occurs during a specific period in time. Often, awareness-raising interventions are organized by an organization or group of organizations.
The goal of this type of initiative is to raise awareness and open a dialogue on mental health and illness. Unfortunately, these types of programs are often not evaluated, so it is difficult to know what kind of effect they have and whether their objectives were met.
World Mental Health Day
The World Health Organization has designated October 10 as World Mental Health Day. All stakeholders working in mental health are encouraged to talk openly about their work, to raise awareness of mental health concerns around the globe, and to discuss ways to improve mental healthcare access.

Contact-Based Interventions
Across a wide range of stigmatizing conditions, people without the stigmatized conditions have little meaningful contact with those who have these conditions. Lack of contact fosters discomfort, distrust, and fear. Contact-based anti-stigma campaigns are one way to foster connection and facilitate positive interactions.
Contact-based education involves people with lived experience of mental illness educating students by sharing their personal stories with positive recovery messages. Contact-based anti-stigma campaigns have been shown to reduce stigma at the individual level. This type of intervention can raise awareness and correct misconceptions, though there is mixed evidence regarding its ability to change behaviours and maintain change long-term. As a result, contact-based education does not often reduce stigma at the macro- or structural-level.
However, the value of contact-based anti-stigma education at the individual level should not be dismissed. For adolescents and emerging adults, fostering connection in an online setting may be beneficial and appealing. The internet is often able to provide anonymity which is preferred by patients (especially when first seeking a connection). In general, the effects of contact in person are higher than those by video or online, but some still prefer the online option.
Contact-based campaigns are often combined with educational and mental health literacy initiatives. This involves information being presented, and then people with lived experience supporting and personalizing the information by relating it to their own life experiences. Although combined interventions generally show an advantage over educational interventions alone, they are implemented less often.

Peer Advocacy/Services
These interventions are based on the same concept as contact-based campaigns: that social connection and positive interactions can contribute to reducing stigma.
Peer service providers are people with lived experience who work as health care team members and foster the provision of nonjudgmental, non-discriminatory services while openly identifying their own experiences. An example is the grassroots organization Active Minds, a college student mental health advocacy group based in the United States (see the video below for more info). Peer support also aims to counterbalance discrimination, rejection and isolation individuals may feel when seeking mental health support or treatment.
2.5 Section Summary
- There are many types of stigma related to mental illness: public stigma, self-stigma, structural stigma, and stigma-by-association. Public stigma is the typical definition of stigma, which highlights the views of the public towards mental health issues or a specific condition. Self-stigma occurs when an individual internalizes the negative stereotypes associated with their illness. Structural stigma is introduced by large, societal structures (e.g., laws, policies, practices that result in unfair treatment). Stigma-by-association occurs when an indiviudal is stigamtized as a result of their elationship with a member of a stigmatized group (e.g., indidviudals living with mental illnesses).
- Stigma can have many harms and societal consequences, including: the formation of serious barriers to help seeking and recieving proper diagnoses and treatment; unemployment resutling in lack of income and financial stability, as well as daily routines/structure and sense of purpose; and intersectional impacts for those who are stigmatized for other reasons, such as race, gender, or sexuality.
- Many types of anti-stigma interventions were introduced in this module, including: mental health education, mental health literacy, awareness-raising campaigns, contact-based interventions, and peer advocacy/services.
Module Contributors
Amy Ecclestone
PhD Candidate, Health Sciences
University of Waterloo
Role: Content Developer
Jessica Rose
Bachelor of Health Sciences
Queen's University
Role: Content Developer
Cristina Rosaria White
Bachelor of Medical Sciences
Western University
Role: Content Developer
Ainsley Johnstone
Bachelor of Health Sciences
Queen's University
Role: Content Developer
Health Sciences and Policy Research Institute
Queen's University
Role: Subject Matter Expert